
Insulin: the basics
What is it?
A natural hormone that helps glucose enter cells. Prescription insulin replaces or supplements it when the body cannot make or use enough.
Research paper ↗What do people claim it helps with?
Blood-sugar control in diabetes is an established, often essential use. Bodybuilding claims do not make nonmedical use safe.
What has research actually shown?
Extensive human evidence supports diabetes treatment. Intensive glucose management reduced complications in type 1 diabetes, while also increasing low-blood-sugar risk in the landmark trial.
Research paper ↗Has this been demonstrated in people?
Demonstrated in people, including controlled clinical trials for the uses described here. Evidence for one diagnosis does not establish benefit for every other claim.
Research paper ↗What side effects, risks and unknowns should I understand?
Low blood sugar can be life-threatening. Weight gain, injection-site changes and low potassium can occur. Different products, meals, exercise and illness affect insulin needs.
Prescribing information ↗Is it an approved medicine?
Yes. Many FDA-approved insulin medicines treat diabetes. Approval belongs to the specific regulated product, not any vial labeled “insulin.”
Prescribing information ↗Approval here means U.S. FDA approval and applies to a particular product, formulation and use. This is a starting overview, not a complete side-effect list. Sources checked 10 October 2026; independent scientific review pending.
How is it used or studied?
Prescription products with different speeds and durations, commonly given by injection or pump; some formulations are inhaled.
Different routes and formulations can have different effects. A study of one product does not validate every product with the same peptide name.
A common misunderstanding
Rapid-acting, long-acting and other insulins are not freely interchangeable.
What should I ask a clinician?
- What diagnosis or goal are we trying to address, and what established options are available?
- Was the expected benefit shown in people like me, using this exact product?
- How could my medicines, health conditions or pregnancy plans affect the risks?
- What monitoring is needed, and what would tell us the treatment is helping or should be stopped?
What do the research words mean?
- Peptide
- A short chain of amino acids, the building blocks of proteins.
- Preclinical
- Research in cells, tissues or animals before dependable treatment evidence in people.
- Controlled trial
- A study comparing a treatment with another treatment or a placebo to help separate its effects from other explanations.
- Biomarker
- A measurement, such as a hormone level. A change does not necessarily mean someone feels better or lives longer.
Insulin Evidence & Clinical Profile
Established Clinical Trials
Insulin has been investigated in clinical contexts. Patient outcomes must be evaluated against study size, design, and control cohorts.
Laboratory & In Vivo Assays
Cellular and animal disease models examine receptor binding affinities and signaling cascades, which require human confirmation.
What is Insulin?
Human Insulin (Regular / NPH / Analogues) is An essential two-chain peptide hormone produced by pancreatic beta cells. Composed of an A-chain (21 amino acids) and a B-chain (30 amino acids) connected by two interchain disulfide bonds. The definitive life-sustaining therapy for type 1 diabetes and advanced type 2 diabetes. Aliases include: Humulin, Novolin, Recombinant Human Insulin, Pancreatic beta-cell peptide hormone.
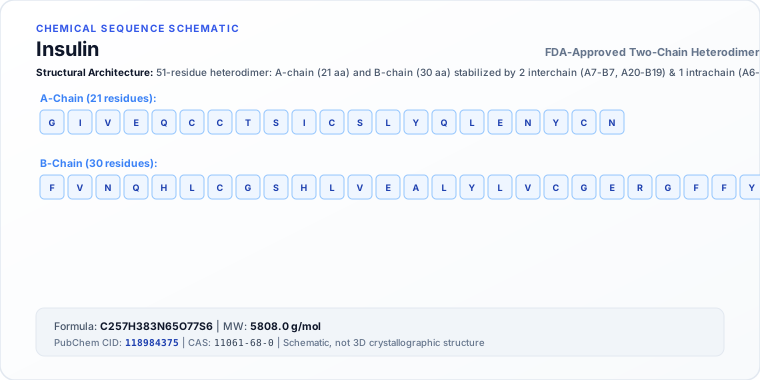
- Sequence (one-letter)
- A:GIVEQCCTSICSLYQLENYCN / B:FVNQHLCGSHLVEALYLVCGERGFFYTPKT
- Molecular formula
- C257H383N65O77S6
- Molecular weight
- 5807.6 g/mol
- CAS Number
- 11061-68-0
- UNII Code
- 1Y17CTI5SR
- PubChem CID
- 118984375
Identifiers are for human insulin. Insulin analogues and animal insulins have their own identifiers.
Identifiers checked against PubChem and FDA's Global Substance Registration System on 13 October 2026. FDA substance record ↗ · PubChem record ↗ See all names and codes in the peptide name index.
Clinical Trials & Human Cohorts
Human research can examine tolerability, symptoms or patient outcomes. The design and comparator determine what each result can establish.
The Effect of Intensive Treatment of Diabetes on the Development and Progression of Long-Term Complications in Insulin-Dependent Diabetes Mellitus [1]
What was reported
Intensive insulin therapy reduced the risk of developing retinopathy by 76% in the primary-prevention cohort and, across both cohorts, reduced microalbuminuria by 39% and clinical neuropathy by 60%.
What limits the conclusion
Severe hypoglycemia increased two- to threefold with intensive therapy.
Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes (UKPDS 33) [2]
What was reported
Over 10 years (median HbA1c 7.0% vs 7.9%), intensive control with sulphonylureas or insulin lowered microvascular endpoints by 25% versus conventional diet-based treatment.
What limits the conclusion
No significant reduction in macrovascular disease; more hypoglycaemia and greater weight gain (4.0 kg in the insulin group).
How the compound may work
Mechanisms describe how Insulin may affect biological processes. Laboratory findings and patient outcomes answer different questions.
Insulin Receptor (INSR) Tyrosine Kinase Activation
Binds the alpha-subunit of the tetrameric INSR, inducing trans-autophosphorylation of beta-subunit tyrosine kinase domains. [3]
IRS-1/PI3K/Akt Driven GLUT4 Translocation
Phosphorylates insulin receptor substrate 1 (IRS-1), activating PI3-kinase and protein kinase B (Akt), which stimulates translocation of glucose transporter 4 (GLUT4) vesicles to the plasma membrane. [3]
Areas Being Studied
These research topics reflect active areas of scientific exploration, distinct from unverified commercial marketing claims.
Type 1 Diabetes Management
Intensive therapy by external insulin pump or three or more daily injections, guided by frequent glucose monitoring, delayed diabetic retinopathy, nephropathy and neuropathy. [1]
Complications in Type 2 Diabetes
Intensive glucose control with sulphonylureas or insulin reduced microvascular but not macrovascular complications. [2]
Compare the study designs.
| Study | Design / sample | Outcome type | Key limitation |
|---|---|---|---|
| DCCT Landmark Trial · 1993 [1] | Multicenter prospective randomized controlled trial n = 1441 |
Clinical endpoint evaluation | Severe hypoglycemia increased two- to threefold with intensive therapy. |
| UKPDS 33 Trial · 1998 [2] | Randomized controlled clinical trial n = 3867 |
Clinical endpoint evaluation | No significant reduction in macrovascular disease; more hypoglycaemia and greater weight gain (4.0 kg in the insulin group). |
Regulatory Status & Clinical Safety
Regulatory Classification
FDA approved across multiple BLAs. Prohibited in competitive sport under WADA Section S4.5 (Metabolic Modulators) without an approved Therapeutic Use Exemption (TUE).
Safety Realities & Impurities
Safety depends on the molecule, formulation, route and evidence. A laboratory purity measurement alone cannot establish safety for human use.
Clinical Trials Registry Records
Official registry records from ClinicalTrials.gov. Study registration does not imply government endorsement or guaranteed efficacy.
Diabetes Control and Complications Trial (DCCT) [1]
- Planned enrollment
- 1441 (patients)
- Posted results
- Pending in registry
- Sponsor
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK)
- Last updated
- 2010
WADA & Anti-Doping Regulations
WADA Section S4: Prohibited Substance
The World Anti-Doping Agency (WADA) classifies Insulin under Section S4 of the Prohibited List. Prohibited at all times (in- and out-of-competition). Last verified: October 2026.
Research Timeline
What Researchers Still Don't Know
Long-term safety profiles
Multi-year observational data in broader heterogeneous cohorts remains uncharacterized.
Optimal dose-response thresholds
Comparative trials optimizing minimal effective exposure versus adverse event rates.
Formulation bioavailability
Differences between oral, subcutaneous, and modified peptide delivery vehicles.
References
Primary sources verified against PubMed / NLM and regulatory databases.
- Landmark RCT
- Landmark Trial
-
Cellular Biology Review
Mechanisms of insulin action and insulin resistance ↗ (external website)
-
Regulatory
CDER Biologics License Application Overview: Insulin Products ↗ (external website)